We partner exclusively with post-acute and senior care organizations to deliver tailored, high-impact solutions across clinical, financial, and operational domains.
This post was updated on September 29, 2026.
For skilled nursing organizations, revenue cycle performance is increasingly determined by what happens before a claim is ever submitted.
Accurate intake, authorization management, interdisciplinary claim review, and ongoing financial analytics all play a role in protecting reimbursement. When one of these processes breaks down, the result can be delayed payment, preventable denials, avoidable administrative work, or revenue that is difficult to recover — often called revenue leakage.
Heading into 2027, the stakes are particularly high as skilled nursing providers manage increasingly complex payer requirements, including Medicare Advantage authorization processes and Medicaid-pending residents. At the same time, the Patient Driven Payment Model (PDPM) continues to make the connection between clinical documentation, MDS coding, and reimbursement critically important.
A disciplined revenue cycle approach starts with four core controls: clean front-end intake, authorization tracking, a strong triple-check process, and data-driven performance management.
The sections that follow break down each control — what it involves, why it matters, and how to put it into practice.
Revenue cycle problems often begin at admission.
A clean intake process should do more than collect a resident’s basic demographic information. Before services begin, the facility should establish a complete and accurate picture of the resident, the payer, and the coverage requirements associated with the stay.
At a minimum, the front-end intake process should verify:
This information creates the foundation for everything that follows. If the payer is wrong, eligibility is not confirmed, an authorization requirement is missed, or a secondary payer is overlooked, the problem can follow the account throughout the resident’s stay.
Medicare Advantage has made payer verification and authorization management increasingly important. Medicare Advantage insurers made nearly 53 million prior-authorization determinations in 2024, and 4.1 million — 7.7% — were denied in full or in part. The volume of determinations has grown alongside Medicare Advantage enrollment. (KFF)
Medicaid Pending cases create another layer of risk. As eligibility reviews tighten, documentation scrutiny increases, and unresolved pending balances draw closer attention, early identification and ongoing case management become especially important — an area where specialized Medicaid eligibility services can help facilities resolve pending cases before they become write-offs. For a deeper discussion, see Medicaid Pending in 2026: New Risks, Greater Scrutiny, Higher Stakes.
The takeaway is straightforward: the earlier a payer or eligibility problem is identified, the more options the organization has to resolve it before it becomes an aged receivable or denial.
Authorization management should not end when the initial authorization is received.
For many skilled nursing organizations, authorization tracking needs to continue throughout the resident’s stay — monitoring the initial approval, subsequent concurrent or continued-stay reviews, authorized days, expiration dates, changes in payer requirements, and any additional documentation requested by the plan. Obtain written confirmation of each authorization and store it in the resident’s record.
A strong authorization process should answer four questions at any point during the stay:
That final question is particularly important. An authorization can be valid at admission and still become a revenue-cycle problem later — a resident may remain in the facility after the approved period ends while the team waits for a continued-stay determination or fails to submit the required clinical information on time.
An effective authorization tracker should include:
The lesson for SNFs is not that every authorization will be denied. Rather, authorization volume and administrative complexity require a process that actively monitors approvals throughout the stay. A good authorization workflow therefore treats expiration dates as financial deadlines — not simply administrative dates.
The triple check should be more than a final glance at the claim.
Done correctly, it is an interdisciplinary review — typically involving MDS coordinators, therapy, nursing/clinical leadership, and the business office — designed to make sure the clinical record, MDS, physician orders, therapy documentation, payer information, and claim tell the same story. Run it on a structured, recurring cadence with defined responsibilities and ongoing staff training.
PDPM makes this particularly important. CMS implemented PDPM for SNF Part A stays beginning October 1, 2019, replacing RUG-IV and shifting the payment methodology toward patient characteristics and clinical factors, including diagnosis and other resident information. (CMS)
CMS has also specifically identified SNF billing errors associated with the transition to PDPM as an area of concern. In its 2023 SNF 5-Claim Probe and Educate initiative, CMS reported a projected SNF improper payment rate of 15.1% for 2022, compared with 7.79% in 2021, and cited potential misunderstanding of PDPM billing requirements as one factor. (CMS)
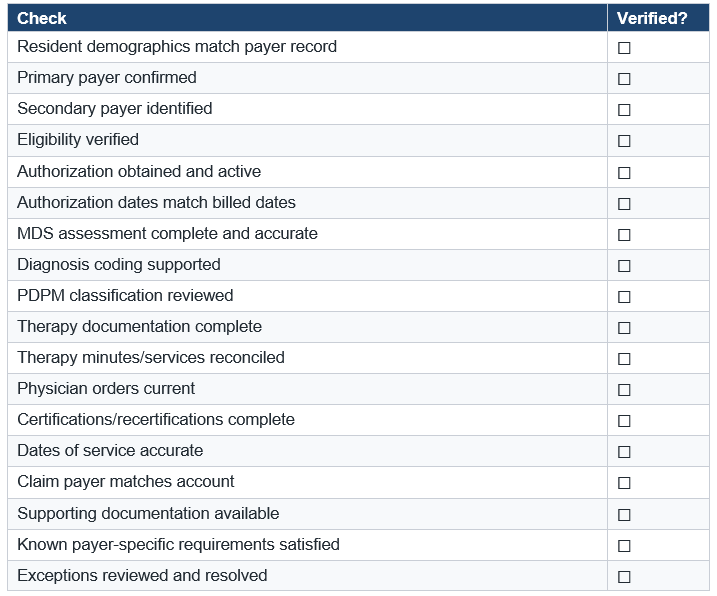
Use a checklist like this before releasing a claim:

The goal is not simply to catch billing errors. The goal is to establish a single, consistent story across the resident’s clinical record, MDS, authorization, and claim.
Under the SNF Prospective Payment System (PPS), most services a resident receives during a covered Part A stay must be billed by the facility rather than separately by outside providers. When an outside provider bills Medicare directly for a service that should have been bundled, it creates duplicate-billing and compliance exposure. Confirm that ancillary and outside services are appropriately captured under consolidated billing before the claim is released — a step that is easy to miss and costly to unwind.
A revenue cycle dashboard is only useful if someone acts on what it shows.
Organizations should establish a small group of financial and operational metrics that are reviewed consistently, assigned to owners, and connected to specific corrective actions. Four particularly useful measures are days in AR, denial rate, clean claim rate, and net collection rate, supported by an analysis of aged AR buckets.
Days in accounts receivable measures how long it takes the organization to convert billed services into cash.
Richter identifies 45 days as an industry-average reference point, while also noting that the appropriate benchmark varies according to billing frequency and payer mix.
Rather than focusing only on the overall number, leadership should also ask:
A stable or declining days-in-AR trend generally provides more useful information than a single month’s result.
Denial rate measures the percentage of submitted claims or dollars that payers deny.
Richter cites an industry denial range of 6%–13% and identifies 3%–5% as a target range for skilled nursing organizations. The more important question, however, is why claims are being denied.
Track denial categories such as:
Eligibility
Authorization
Incorrect payer
Missing documentation
Coding
Medical necessity
Timely filing
Duplicate claims
MDS/claim discrepancies
A declining denial rate is useful, but a declining preventable denial rate is even more informative.
A denial is not the end of the story. Build a closed-loop process: appeal eligible denials before the filing deadline, and feed the root cause of each denial back to the front-end or clinical step that produced it. Track appeal overturn rate alongside denial rate — a high overturn rate signals denials that were preventable or wrongly denied, and quantifies the revenue at stake in your appeals process.
Clean claim rate measures how many claims can be submitted and processed without requiring correction or additional information.
A strong clean-claim process should produce consistently high first-pass acceptance. If the rate falls, investigate whether the cause is concentrated in a particular payer, facility, workflow, employee, or claim type. Clean claims are one of the clearest indicators that front-end intake, authorization management, clinical documentation, and billing controls are working together.
Net collection rate helps answer a fundamental question: of the collectible revenue the organization expects to receive, how much is it actually collecting?
A strong net collection rate should remain consistently high and should be evaluated alongside contractual adjustments, bad debt, payer mix, and aged AR. If collections are falling while billed revenue remains stable, leadership should look beyond the general ledger and examine what is happening in the revenue cycle.
Never look at total AR alone. Break the balance into aging categories — for example:
Then segment those balances by payer. This can reveal problems that an overall AR number hides. A facility may have acceptable total AR while simultaneously accumulating an increasingly large Medicaid Pending or Medicare Advantage balance in the 90+ day category.
PointClickCare emphasizes the value of using analytics to connect clinical, financial, and operational information rather than treating reporting as a retrospective exercise. Its analytics resources highlight areas such as reimbursement, PDPM optimization, case mix, staffing, census, and operational performance.
5 Essential Back-Office KPIs Every Skilled Nursing Organization CFO Should Monitor provides additional guidance on financial metrics and benchmarks. For organizations using PointClickCare, Using PointClickCare® Analytics to Drive Better Clinical and Financial Decisions offers additional perspective on turning available data into operational decisions.
The key is to establish an operating rhythm:
These four controls are interconnected.
A clean admission reduces eligibility and payer errors. Strong authorization tracking prevents avoidable mid-stay gaps. A disciplined triple check catches discrepancies before claims leave the building. And meaningful analytics tells leadership whether those controls are actually working.
The most effective revenue cycle strategy is therefore not simply “bill faster.” It is to create a process in which accurate information enters the organization early, remains accurate throughout the resident’s stay, and is validated before the claim is submitted.
For skilled nursing organizations navigating Medicare Advantage, Medicaid Pending, PDPM, and increasingly complex payer requirements, that level of discipline can make the difference between simply generating claims and consistently converting care into collectible revenue.
Richter identifies roughly 45 days as an industry-average reference point, though the appropriate target varies with billing frequency and payer mix. Tracking the trend and the share of AR over 90 days is more useful than any single month’s number.
Industry denial rates generally range from 6%–13%, with 3%–5% a reasonable target for skilled nursing organizations. Tracking preventable denials by category matters more than the overall rate alone.
The triple check is an interdisciplinary pre-bill review — involving MDS, therapy, nursing/clinical, and the business office — that confirms the clinical record, MDS, physician orders, therapy documentation, authorization, and claim all tell the same story before submission.
Under PDPM (effective October 1, 2019), reimbursement is driven by patient characteristics and clinical factors captured on the MDS. CMS has cited misunderstanding of PDPM billing as a factor in a rising SNF improper payment rate, so MDS-to-claim accuracy directly affects both compliance and revenue.
Richter’s revenue cycle and accounting specialists help skilled nursing and senior living organizations tighten every stage of the revenue cycle — from front-end intake and authorization management to denial resolution, KPI reporting, and full outsourced billing support. Contact us to learn how we can help protect your reimbursement and strengthen financial performance.
KFF — Medicare Advantage Insurers Made Nearly 53 Million Prior Authorization Determinations in 2024
CMS — Skilled Nursing Facility 5-Claim Probe and Educate Review
Jodie Abbinante
Business Development Representative
Schedule your complimentary 30 minute discovery call so our team can learn about your goals and how we might be able to help.
Subscribe to our newsletter to receive the latest articles and updates aimed at helping you enhance operational, clinical and financial outcomes.